

Loading…
Loading…
Loading…
Edexcel GCSE History · 1HI0
Edexcel 1HI0 · Factors Affecting Medical Development Check the specification (PDF) (opens in a new tab)
Medical change rarely resulted from one person working alone. An individual might discover a promising treatment, but scientific testing was needed to establish whether it worked. Manufacturers then needed suitable technology to produce it, while institutions could supply money and organise its use. Society’s priorities influenced whether that work received urgent attention.
These are interacting factors: one factor makes another more effective. Factors could also reinforce barriers to change. Comparing responses to epidemics with the development of penicillin shows how their relationships changed over time.
The Black Death reached Britain in 1348. Without knowledge of the microbes causing plague, people explained it through familiar beliefs, including punishment from God and miasma—bad or corrupted air thought to cause disease.
Religious attitudes and the Church’s authority worked together. Belief in divine punishment made prayer and repentance seem appropriate responses, while the Church encouraged people to confess their sins and pray for forgiveness. These actions addressed the supposed spiritual cause rather than providing an effective treatment for plague.
Miasma theory also linked explanation to action. People carried flowers or strong-smelling herbs, or moved to the countryside to escape supposedly corrupted air. Their responses were not random: they followed logically from an incorrect understanding of disease.
Government action was limited rather than entirely absent. Gloucester attempted to close itself off to outsiders, but people ignored the restriction. This illustrates an important interaction: an institution’s decision depended on public compliance to become effective. An order alone did not guarantee successful prevention.
During the Great Plague of 1665, religious explanations and miasma theory remained influential. People still prayed and used herbal remedies, while officials ordered fires to be lit in the streets to combat supposed bad air. Greater government activity therefore did not necessarily mean more accurate medical knowledge.
Charles II issued a royal decree, and local officials organised its enforcement. Infected houses were marked with red crosses and placed under a 28-day quarantine. Quarantine means separating infected or potentially infected people from others. Watchmen guarded houses, searchers identified plague deaths, and theatres and public gatherings were banned.
Here, central authority and local organisation worked together: royal rules became practical measures through officials and hired workers. Compared with Gloucester’s unsuccessful attempt to exclude outsiders in 1348, the use of watchmen in 1665 shows a more organised attempt to enforce restrictions.
There was nevertheless substantial continuity. In both epidemics, mistaken beliefs shaped prevention, and there was no effective cure. Institutional change could improve the organisation of a response without transforming understanding or treatment.
Cholera reached Britain in 1831 and spread in overcrowded towns with poor sanitation. It is a disease spread through contaminated water, but many contemporaries blamed miasma. During the severe outbreak of 1848–49, the government passed the 1848 Public Health Act. It encouraged local improvements, but its largely non-compulsory approach limited implementation.
In 1854, the London doctor John Snow investigated cholera deaths in Soho. He plotted deaths on a spot map and identified a concentration around the Broad Street water pump. This supported his argument that contaminated drinking water, rather than bad air, spread cholera.
Snow’s work connected an individual’s investigation with systematic evidence. However, evidence of a geographical pattern was different from identifying the microorganism responsible. His findings did not immediately overturn established attitudes or produce a comprehensive government response.
Other developments helped change the context. The Great Stink of 1858 increased pressure on government to deal with London’s sewage. Pasteur’s germ theory of 1861 supplied a scientific framework for understanding how microorganisms could cause disease. The 1875 Public Health Act made local provision of clean water and sanitation compulsory.
The interaction was therefore broader than ‘Snow solved cholera’: investigation challenged an established explanation, scientific developments strengthened understanding, and government action helped turn prevention into public provision. Scientific knowledge and institutional implementation were separate but connected achievements.
In 1928, Alexander Fleming was studying Staphylococcus bacteria at St Mary’s Hospital in London. He noticed that mould contaminating a culture dish had prevented bacteria from growing around it. This observation led to his discovery of penicillin, and he published his findings in 1929.
Chance helped create the opportunity, but Fleming’s scientific knowledge mattered: he recognised that the pattern of bacterial growth was significant. An accidental observation alone would not have produced a medical advance.
Nevertheless, publication did not immediately turn penicillin into a practical treatment. Researchers still needed to demonstrate its effectiveness in living organisms and obtain enough of it for patients. This distinction explains the importance of the next stage.
In 1939, Howard Florey and Ernst Chain at Oxford took up Fleming’s work. Their different scientific expertise helped them investigate penicillin together. Successful tests on mice in 1940 provided evidence that it could work against infection in a living animal.
In 1941, they used penicillin to treat a policeman, Albert Alexander. His condition initially improved, but the supply ran out and he died. The episode revealed both the treatment’s promise and a crucial limitation: a medicine could not reliably save patients if there was too little to complete treatment.
Here, individuals and science worked together. Fleming supplied the original finding; the Oxford team developed and tested it. Their work also exposed a problem that laboratory research alone could not solve: production on a much larger scale.
The Second World War increased the urgency of finding effective treatments for infected wounds. Saving wounded soldiers made penicillin an immediate priority rather than simply an interesting research possibility.
In July 1941, Florey travelled to the United States to seek help from pharmaceutical companies. British and American government support helped fund research and production. Manufacturers used large vessels, including vats, to grow the mould and produce penicillin in greater quantities. By 1945, the US Army had access to about two million doses each month.
The connection is important: wartime need encouraged institutional support; funding and industrial technology enabled large-scale production; production made the scientists’ discovery useful to many more patients. Neither money without a working treatment nor a working treatment without adequate supplies would have achieved the same result.
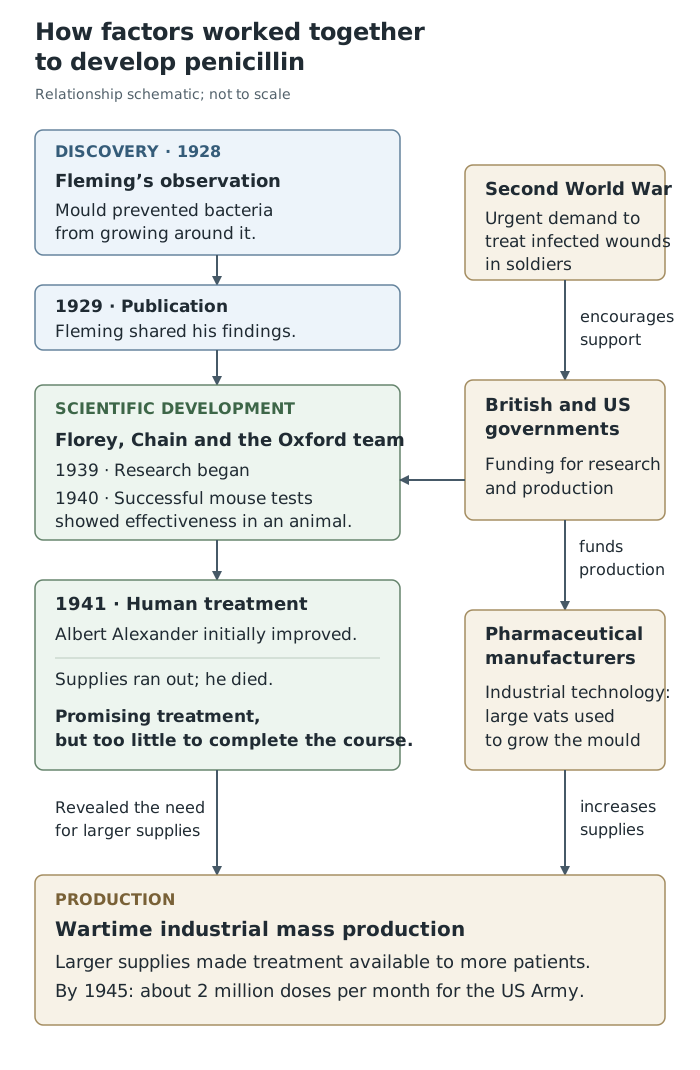
Penicillin became widely usable through linked contributions, not through discovery alone.
A useful comparison identifies a shared feature and explains it using evidence from both periods. For example, official responses to the Great Plague and nineteenth-century cholera both included measures influenced by miasma theory: street fires in 1665 and efforts to clean unhealthy urban areas during cholera outbreaks. Government involvement could therefore coexist with mistaken explanations of disease.
A difference emerges when comparing later cholera prevention with plague prevention. In 1665, officials enforced temporary restrictions on infected households and gatherings. By 1875, compulsory provision of clean water and sanitation addressed conditions that allowed waterborne disease to spread. Government responsibility had extended beyond managing an immediate outbreak towards sustained public-health provision.
Treatment also offers a useful comparison. In the nineteenth century, Pasteur’s work on germ theory helped provide a scientific explanation for infection. Joseph Lister applied this understanding to surgery, using carbolic acid as an antiseptic to reduce infection in wounds. In the twentieth century, Florey and Chain developed penicillin as an antibiotic that could act against bacteria inside the body.
There was continuity in the importance of scientific understanding combined with individuals applying it to treatment. However, the methods differed: antiseptics reduced infection in the surgical setting, whereas penicillin treated bacterial infection within the patient. Penicillin’s wartime expansion also depended on government-backed industrial production.
These comparisons are more precise than saying that medicine simply became ‘better’. They distinguish beliefs, organisation, prevention and treatment, which did not all change at the same speed.
For the original discovery of penicillin, Fleming’s observation was central. For its development into a usable treatment, Florey and Chain’s research and teamwork were crucial. For wartime availability, government support and manufacturing technology became especially important.
Availability is also different from access. The NHS, introduced by Aneurin Bevan and the Labour government in 1948, made medical care free at the point of use. This was an institutional change in how people obtained care, rather than the discovery of a new drug. Comparing these developments helps explain why no single factor can account for every kind of medical progress.
Interaction: scientific discovery → testing and development → funded manufacture → wider treatment.
Discovery, development, production and access are distinct. The NHS, 1948, improved access through free care at the point of use; it did not discover penicillin.
Explain the link between factors: government funding enabled scientists and manufacturers to develop and produce a treatment. Simply naming several factors does not explain their interaction.
Distinguish Fleming’s discovery of penicillin from Florey and Chain’s development of it into a usable treatment.
For a comparison, identify a precise similarity or difference and support it with evidence from both periods.
Judge importance against the outcome being explained: discovering a substance, producing enough of it and making treatment accessible are different achievements.
Distinguish evidence linking cholera to contaminated water from a scientific explanation of the microbes causing it. Snow’s investigation preceded Pasteur’s germ theory.
It can see this note and what your specification asks for.
Answers are free with an account.
1 free note left this week
Get more free notesYour answer sets when this note comes back for review, or marks it complete.
Was this note helpful?
Log in to tell us whether it helped, or to report a problem.
Last updated
Factor
A circumstance, person or organisation that encourages or inhibits historical change.
Factor interaction
The way two or more influences work together, with one enabling, strengthening or limiting another.
Antibiotic
A medicine that kills bacteria or stops their growth, used to treat bacterial infections.
Antiseptic
A substance used to kill microbes and reduce the risk of infection, for example in a wound during surgery.
Mass production
Manufacturing a product in large quantities rather than making small amounts for research or individual use.
Miasma theory
The belief that disease was caused by bad or corrupted air.
Quarantine
Separating people who are infected, or may be infected, from others to limit the spread of disease.
Put your knowledge into practice — try past paper questions for History
Factor
A circumstance, person or organisation that encourages or inhibits historical change.
Factor interaction
The way two or more influences work together, with one enabling, strengthening or limiting another.
Antibiotic
A medicine that kills bacteria or stops their growth, used to treat bacterial infections.
Antiseptic
A substance used to kill microbes and reduce the risk of infection, for example in a wound during surgery.
Mass production
Manufacturing a product in large quantities rather than making small amounts for research or individual use.
Miasma theory
The belief that disease was caused by bad or corrupted air.
Quarantine
Separating people who are infected, or may be infected, from others to limit the spread of disease.