

Loading…
Loading…
Loading…
Edexcel GCSE History · 1HI0
Edexcel 1HI0 · Injuries, Treatment and the Trenches Check the specification (PDF) (opens in a new tab)
On the British sector of the Western Front in Flanders and northern France during 1914–18, wounded soldiers needed both treatment and transport. Immediate first aid near the fighting could help a casualty survive, but serious injuries required facilities that could not all be provided in a front-line trench.
The chain of evacuation linked medical posts near the front to better-equipped hospitals farther away. Its aims were to return soldiers with treatable minor injuries to duty and move more seriously wounded men away from the fighting for further care. It was not simply a journey to hospital: treatment and decisions about what should happen next took place along the route.
The Royal Army Medical Corps (RAMC) organised medical treatment and transport. Medical officers examined and treated casualties, while stretcher bearers carried men who could not walk. A wounded soldier's ability to walk therefore affected how he reached medical help.
Nurses worked alongside doctors in casualty clearing stations and base hospitals. They also worked at dressing stations from 1915. Their work helped sustain care beyond the casualty's first emergency treatment: moving a man away from danger was only useful if medical staff could continue treating and caring for him.
The first treatment stage was usually the regimental aid post (RAP), approximately 200 metres from the front line. It might occupy a trench or an abandoned building. A regimental medical officer and stretcher bearers provided immediate first aid.
Men who could walk made their way there on foot; others arrived on stretchers. More serious cases were sent onwards to dressing stations. The aid post's position made initial help accessible, but it was not a fully equipped hospital.
A field ambulance was a mobile RAMC medical unit, rather than a vehicle. It could treat around 150 wounded soldiers at a time and was responsible for establishing dressing stations.
There were two main dressing-station stages. An advanced dressing station (ADS) was around 400 metres behind the aid post, while a main dressing station (MDS) was around a mile behind it. These distances were approximate, not a fixed layout for every battlefield. Stations often used dug-outs or abandoned buildings for protection from artillery.
Casualties arrived on foot or by stretcher. Medical officers, RAMC stretcher bearers and, from 1915, nurses provided emergency first aid. Men needing more extensive treatment were evacuated to a casualty clearing station. Ambulance vehicles—including horse-drawn and motor ambulances—helped move wounded men along the evacuation chain.
A casualty clearing station (CCS) stood several miles behind the front, often in a factory or school. It was located near a railway so that patients could be transported onwards. Casualties arrived by ambulance wagon, and doctors and nurses were equipped to deal with serious injuries.
Staff used triage to sort casualties by their condition and needs. Walking wounded could receive minor treatment and return to fighting. Men needing hospital care were sent to base hospitals. Those judged too severely wounded to survive were made as comfortable as possible.
This shows why evacuation did not mean that every man followed an identical route. The patient's condition determined whether he returned to duty, continued towards hospital or received care where he was. The scale of the task was enormous: during the Third Battle of Ypres in 1917, 24 casualty clearing stations treated more than 200,000 casualties.
Base hospitals were farther from the fighting, near the French and Belgian coasts. They occupied large buildings or converted civilian hospitals and had doctors, nurses and specialist teams.
Patients travelled there by train or canal barge. These transport links connected the treatment system near the battlefield with hospitals capable of providing further care. Some soldiers were then taken to Britain by hospital ship.
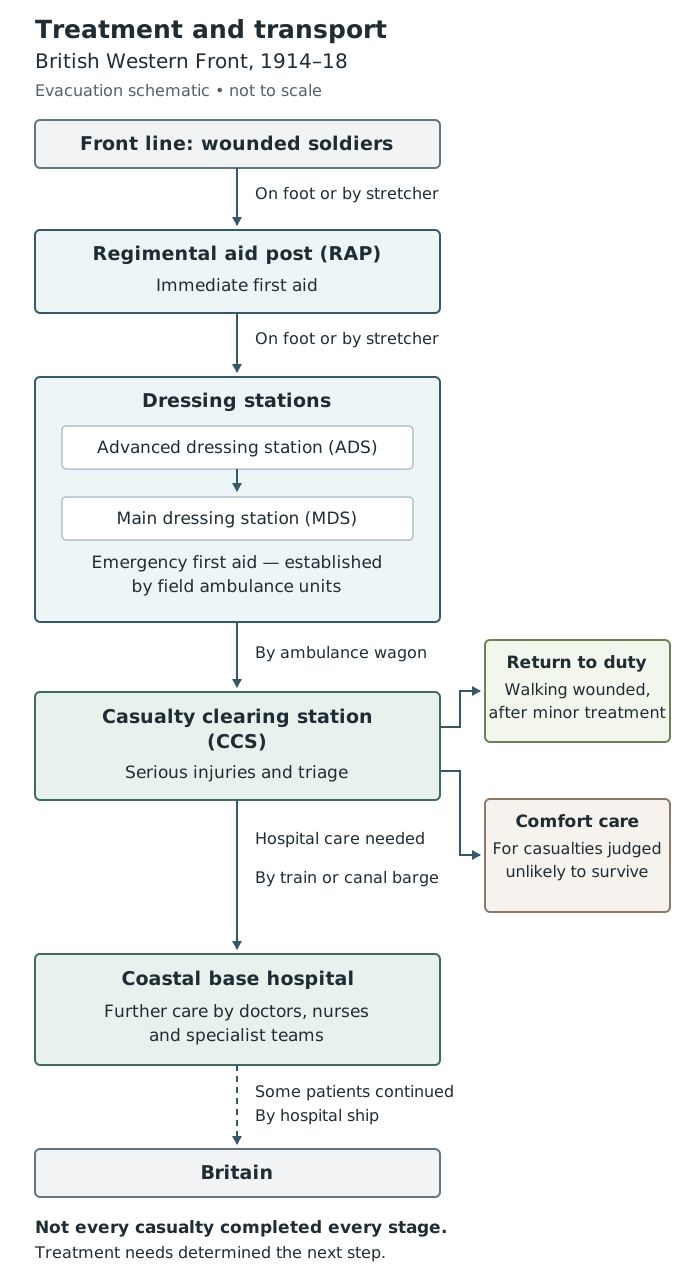
The evacuation chain combined transport with treatment. A casualty's condition determined whether he moved onwards or returned to duty.
Read the chain as a sequence of changing treatment needs, not just increasing distance. Stretcher bearers brought help within reach of men unable to walk; ambulances connected treatment stations; railways and waterways carried casualties towards coastal hospitals. At each stage, staff treated patients and decided whether they needed to move onwards.
During preparations for the Battle of Arras in April 1917, Colonel A. G. Thompson, responsible for the medical service of the British Sixth Corps, organised an underground medical centre in a former chalk quarry. Known as Thompson's Cave, it lay about 20 metres below ground and approximately 730 metres from the front-line trench. It provided sheltered treatment near the fighting, rather than serving as a coastal base hospital.
The hospital was designed to accommodate 700 wounded soldiers. It contained operating rooms, waiting areas for sorting casualties, a morgue and a kitchen. Running water and electric lighting powered by a generator supported medical work underground. RAMC field ambulance units ran the hospital, while RAMC labour personnel worked with New Zealand tunnellers to prepare its floors and access passages.
Two communication trenches led directly to its entrances, which had gas-tight doors. An ambulance shelter stood on the surface. These arrangements linked protected treatment space to the evacuation system. Thompson also pooled the transport resources of different divisions' medical services to move casualties more quickly from the front towards hospitals farther behind the lines.
Underground protection had limits. On 11 April 1917, a shell explosion above the quarry broke a water pipe, causing flooding and collapses. No one was killed, but patients and equipment had to be evacuated that night and the following day. Treatment posts were then established in large buildings. Arras therefore illustrates both the practical adaptation of medical facilities to battlefield conditions and their continuing vulnerability.
Front line → regimental aid post → dressing stations → casualty clearing station → base hospital → Britain for some patients.
A field ambulance was a mobile RAMC medical unit, not a vehicle. Distinguish it from horse-drawn and motor ambulances.
When describing a treatment stage, identify a specific feature and develop it with a relevant detail, such as its staff, treatment or transport links.
Do not assume every casualty passed through every stage: men with minor injuries could return to duty after treatment.
It can see this note and what your specification asks for.
Answers are free with an account.
1 free note left this week
Get more free notesYour answer sets when this note comes back for review, or marks it complete.
Was this note helpful?
Log in to tell us whether it helped, or to report a problem.
Last updated
RAMC
The Royal Army Medical Corps: the British Army organisation responsible for medical treatment and the transport of sick and wounded soldiers.
Chain of evacuation
The organised system for treating and moving wounded soldiers from the front line to progressively better-equipped medical facilities.
Field ambulance
A mobile RAMC medical unit that treated casualties and established dressing stations; it was not an ambulance vehicle.
Triage
The sorting of casualties according to their condition and treatment needs, so that limited medical resources could be allocated.
Put your knowledge into practice — try past paper questions for History
RAMC
The Royal Army Medical Corps: the British Army organisation responsible for medical treatment and the transport of sick and wounded soldiers.
Chain of evacuation
The organised system for treating and moving wounded soldiers from the front line to progressively better-equipped medical facilities.
Field ambulance
A mobile RAMC medical unit that treated casualties and established dressing stations; it was not an ambulance vehicle.
Triage
The sorting of casualties according to their condition and treatment needs, so that limited medical resources could be allocated.