

Loading…
Loading…
Loading…
AQA GCSE Biology · 8461
AQA 8461 · 4.2.2.6 Lifestyle and Disease Check the specification (PDF) (opens in a new tab)
Discuss the human and financial costs of non-communicable diseases locally and globally.
Explain the effect of lifestyle factors (diet, alcohol, smoking) on disease incidence.
Identify risk factors and causal mechanisms for cardiovascular disease, diabetes, liver/brain function, and lung disease/cancer.
Explain the effects of smoking and alcohol on unborn babies.
Understand the principles of sampling in epidemiological data.
A non-communicable disease cannot spread from one organism to another. Examples include coronary heart disease, cancer and type 2 diabetes. Many are long-lasting, so their effects may continue for years rather than ending after a short period of illness.
Their impact can be considered at four connected scales: the individual, the local community, the nation and the world. At each scale, it is useful to separate human costs from financial costs. Money can sometimes reduce suffering—for example, by paying for treatment—but a financial figure cannot fully represent pain, anxiety or loss of life.
Human costs can include pain, disability, reduced independence, poorer quality of life, mental ill health, a reduced lifespan and death. Treatment may also take time and cause unpleasant side effects. Family and friends may experience anxiety, grief or the pressure of providing care.
The individual or family may lose income if illness prevents paid work. They may also pay for travel to appointments, care, medicines not otherwise provided, specialist equipment or alterations to the home. A relative who becomes a carer might reduce their own working hours. These are financial effects even though they occur outside a hospital.
A local community may need more clinics, carers and support services. Schools and workplaces may experience absence, while charities and families may provide additional care. If many people are affected, local health services can face greater demand and longer waits.
At national level, healthcare systems pay for diagnosis, treatment, long-term monitoring and research. In the UK, much of this cost is met through the NHS. Governments may also pay welfare support, while the economy can lose productive work and tax income through illness or premature death. Spending more on one area can leave less money available for other public services.
Globally, the effects accumulate across countries: very large numbers of affected people create a substantial human burden and reduce economic activity. The consequences are not identical everywhere. Access to diagnosis, treatment and long-term care differs, so the same disease may have different effects on people and health systems in different places.
These scales are linked rather than separate. One person’s illness can reduce household income, increase demand for local services and contribute to national healthcare costs. A good discussion follows these links without counting the same cost twice.
Epidemiologists investigate patterns of disease in populations. Studying every person is usually too slow, costly or impractical, so they collect information from a sample and use it to draw conclusions about a larger target population.
For example, an investigation might ask whether people exposed to a possible risk factor have a higher incidence of a disease than people who are not exposed. Researchers could use surveys or medical records rather than examining every member of the population.
The target population must be defined clearly. “Adults in one town during a particular year” is more precise than “people”. The method used to choose the sample then determines how confidently its results can be applied to that target population.
A useful sample should represent the relevant variation within the population. If age, sex or lifestyle could affect the result, the sample should not accidentally contain mainly one group. Researchers may divide the population into relevant groups and select people randomly within each group. This combines coverage of the groups with random selection.
Random selection reduces the researcher’s opportunity to choose participants who support an expected result. It does not guarantee a perfect sample, because chance differences can still occur. A larger sample generally reduces the influence of unusual individuals and random variation, but size cannot repair a badly biased selection method.
A convenience sample—for example, surveying only visitors to one clinic—may differ systematically from the whole population. A voluntary survey can also produce volunteer bias if people with strong views or particular experiences are more likely to respond. Non-response can introduce further bias if those who reply differ from those who do not.
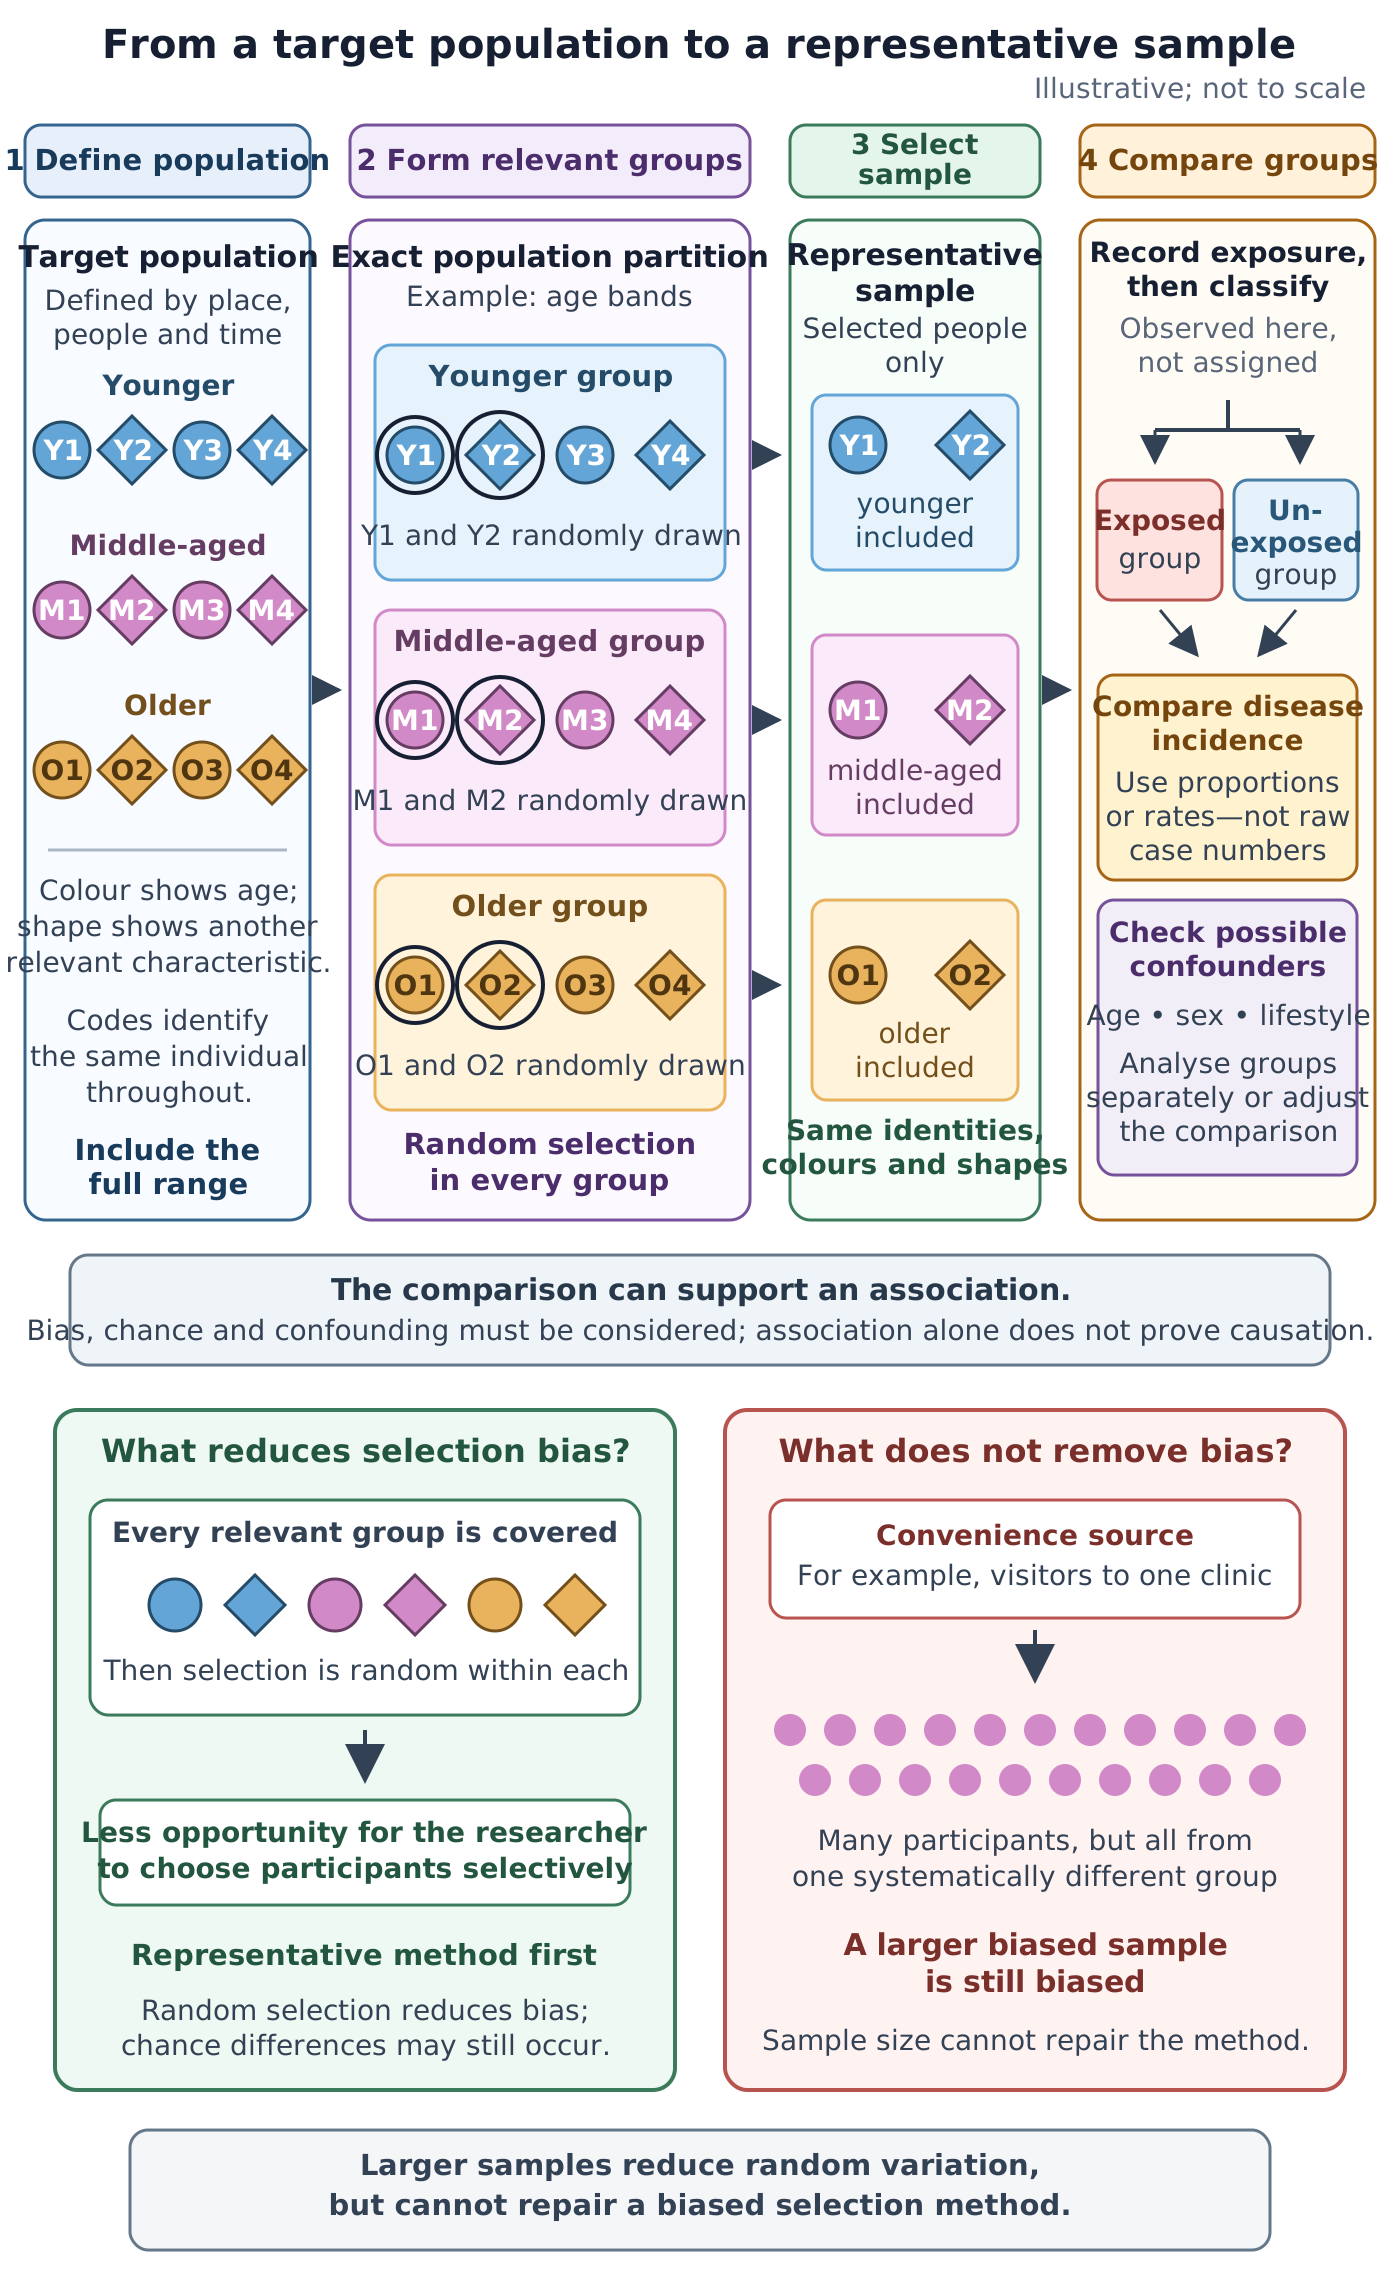
A representative sample covers relevant sections of the target population and uses random selection within them. The selected individuals retain the same characteristics as they move into the sample; researchers then compare disease incidence while considering bias and possible confounding factors.
Suppose a study investigates whether a possible risk factor is associated with a disease. Researchers select participants from several age groups, record exposure to the factor and compare disease incidence in exposed and unexposed groups. If the groups contain different numbers of people, their raw numbers of cases should not be compared directly; proportions or rates provide a fairer comparison.
Other variables may affect the outcome. If the exposed group is older on average, age could be a confounding factor because disease incidence may also vary with age. Researchers can analyse age groups separately or adjust the data to make comparisons more meaningful. Sex and other lifestyle factors may need similar consideration.
Sampling can reveal a pattern in a population, but an association does not by itself prove that the risk factor caused the disease. Bias, chance and confounding variables must be considered, and evidence of a biological causal mechanism may also be needed. Conclusions should therefore match the strength and limits of the data: a study may support an association without proving causation.
A representative sample supports generalisation to its target population. A biased sample may not. An association between a possible risk factor and disease does not alone prove causation: chance, bias and confounding factors must also be considered.
When asked to “discuss” costs, include both human and financial effects and consider more than one scale, such as the individual and the nation.
Do not describe every cost as a healthcare cost. Lost earnings, absence from work, travel and home adaptations are also financial effects.
A large sample is not automatically representative. Explain how participants were selected and whether relevant groups were included.
When evaluating epidemiological evidence, distinguish an association from a proven cause and identify possible confounding factors.
Compare incidence as a proportion or rate when groups contain different numbers of people; raw case totals may be misleading.
It can see this note and what your specification asks for.
Answers are free with an account.
1 free note left this week
Get more free notesYour answer sets when this note comes back for review, or marks it complete.
Was this note helpful?
Log in to tell us whether it helped, or to report a problem.
Last updated
Non-communicable disease
A disease that cannot be passed from one organism to another; many such diseases are long-lasting and may worsen over time.
Incidence
The number of new cases of a disease occurring in a population during a stated period.
Epidemiology
The study of the occurrence, distribution and possible causes of health conditions in populations.
Sample
A smaller group selected from a population to provide data about that population.
Representative sample
A sample whose relevant characteristics reflect those of the target population closely enough to support valid conclusions about it.
Random sampling
Selection in which each eligible member of a population or defined group has an equal chance of being chosen.
Confounding factor
A factor associated with both the factor being investigated and the outcome, which may provide an alternative explanation for an observed relationship.
Bias
A consistent distortion in results caused by the way a study or sample is designed, selected, measured or reported.
Put your knowledge into practice — try past paper questions for Biology
Non-communicable disease
A disease that cannot be passed from one organism to another; many such diseases are long-lasting and may worsen over time.
Incidence
The number of new cases of a disease occurring in a population during a stated period.
Epidemiology
The study of the occurrence, distribution and possible causes of health conditions in populations.
Sample
A smaller group selected from a population to provide data about that population.
Representative sample
A sample whose relevant characteristics reflect those of the target population closely enough to support valid conclusions about it.
Random sampling
Selection in which each eligible member of a population or defined group has an equal chance of being chosen.
Confounding factor
A factor associated with both the factor being investigated and the outcome, which may provide an alternative explanation for an observed relationship.
Bias
A consistent distortion in results caused by the way a study or sample is designed, selected, measured or reported.