

Loading…
Loading…
Loading…
AQA GCSE Biology · 8461
AQA 8461 · 4.2.2.4 Coronary Heart Disease Check the specification (PDF) (opens in a new tab)
Explain the pathology of coronary heart disease and its effect on blood flow.
Evaluate the advantages and disadvantages of treating cardiovascular diseases with drugs, mechanical devices, or transplants.
Describe the use of stents and statins.
Explain the consequences and treatments for faulty heart valves.
Discuss heart transplants and the use of artificial hearts.
The heart works as a pump, and its valves keep blood moving in the correct direction. A healthy valve opens sufficiently when blood needs to pass through and then closes to prevent backflow. This one-way flow helps each heartbeat deliver an effective volume of blood.
A valve can become faulty in two main ways:
In either case, less blood may be moved forwards with each heartbeat. The heart may have to work harder to maintain the circulation, while body tissues may receive less oxygen. With less oxygen available for aerobic respiration, less energy is transferred for processes such as muscle contraction. A person may therefore become tired or short of breath, especially during activity.
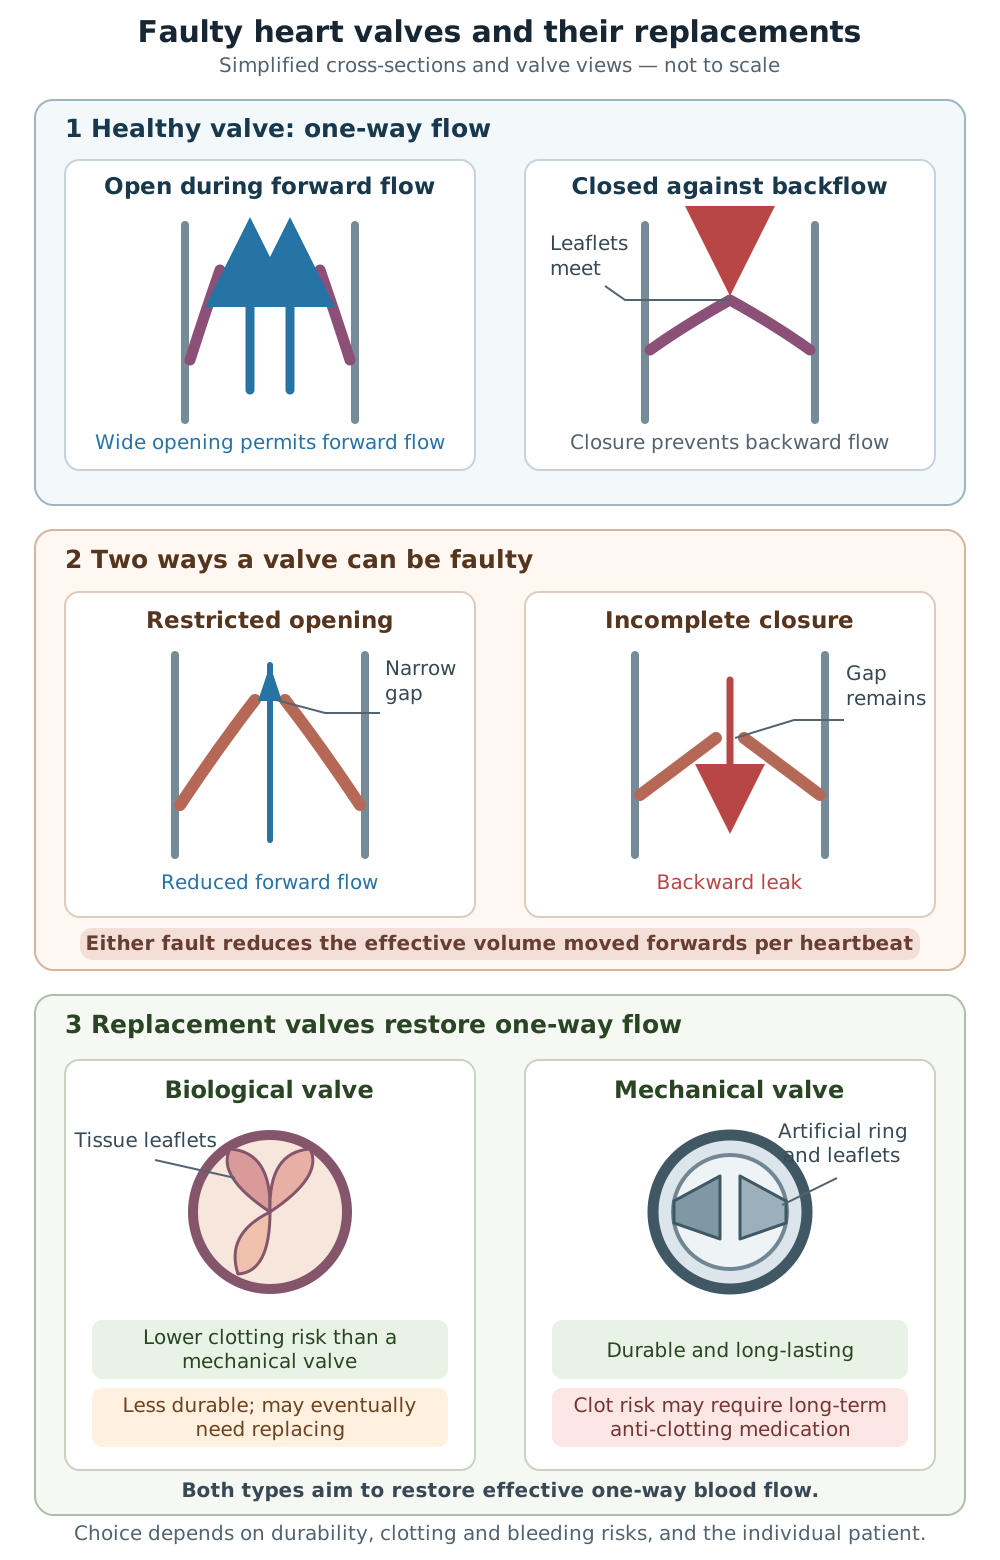
Healthy valves maintain one-way flow. Restricted or leaky valves reduce effective forward flow and may be replaced by biological or mechanical valves.
A severely faulty valve can be removed or bypassed and replaced by either a biological valve or a mechanical valve. Both aim to restore one-way blood flow, but they involve different compromises.
A mechanical valve is made from artificial materials. It is durable and can last a long time. However, blood clots may form around it, so the patient may need long-term anti-clotting medication. That medication lowers the risk of a dangerous clot but can increase the risk of bleeding.
A biological valve is made from animal or human tissue. Blood clots are less likely to form around it, so long-term anti-clotting medication may not be needed for the valve itself. However, biological valves are less durable and may eventually need replacing. Further surgery carries additional risks. The use of animal tissue may also raise ethical or religious concerns for some patients.
Neither choice is automatically best. Durability may be especially important for a younger patient, whereas avoiding long-term anti-clotting medicine may matter more for a patient at high risk of bleeding. Doctors and patients must balance these factors alongside the risks of surgery, such as infection and complications from anaesthesia.
Heart failure means that the heart cannot pump blood effectively enough to meet the body’s needs. If the damage is severe, repairing one valve or treating a narrowed artery may not solve the problem. A donor heart—or, in some cases, a donor heart and lungs—can then be transplanted.
A successful heart transplant can restore effective circulation and greatly improve quality of life and life expectancy. Unlike a mechanical device, the transplanted heart functions as a living organ.
There are important disadvantages. Suitable donor organs are scarce, so a patient may wait a long time and may become more unwell while waiting. The operation itself is major surgery. In addition, the recipient’s immune system can recognise cells in the donor heart as foreign and attack them. This is rejection.
The patient therefore takes immunosuppressant drugs. These reduce the immune response and make rejection less likely, but they also reduce the body’s ability to fight pathogens. This increases the risk of infectious disease. A transplant consequently requires continuing medication and medical monitoring rather than being a completely risk-free cure.
An artificial heart is a mechanical device that supports or replaces the heart’s pumping action. In this course, its main roles are to keep a patient alive while a suitable donor heart is found, or to allow the patient’s own heart to rest and possibly recover.
An artificial heart can be available without waiting for a human donor and is not rejected by the immune system. This can make it a vital option for a critically ill patient. However, fitting it requires surgery, with risks including infection. Contact between blood and the device may also encourage clot formation, and the device requires a power supply. Mechanical parts can wear out, so an artificial heart does not reproduce every advantage of a healthy living organ.
Treatments should be matched to the problem rather than ranked in isolation.
| Approach | Possible advantages | Possible disadvantages |
|---|---|---|
| Drugs | Often relatively inexpensive; usually avoid surgery; can reduce risk or manage disease | May cause side effects; doses may be needed for a long time; effectiveness depends on the patient taking them correctly; may not repair existing structural damage |
| Mechanical devices | Can correct or support a physical function; do not depend on a donor organ; artificial materials are not rejected as donor tissue | Usually require a procedure or surgery; may cause infection or clotting; may need power, medication or later replacement |
| Transplant | A successful donor organ can restore the function of a severely failing heart and improve quality of life | Donors are scarce; major surgery is required; rejection is possible; lifelong immunosuppressants raise infection risk |
The correct conclusion depends on the evidence in the question. Drugs may be appropriate when disease can be controlled without surgery. A replacement valve is more relevant when the problem is a particular faulty valve. For severe heart failure, transplantation may offer the greatest long-term improvement, but an artificial heart may be needed immediately while no donor is available. A strong evaluation weighs how effective each option is against its risks, availability and long-term demands.
A valve may:
Both reduce pumping efficiency. Less oxygen may reach tissues, reducing aerobic respiration and causing tiredness or breathlessness.
Both require surgery and carry risks such as infection.
A donor heart, or sometimes heart and lungs, may be transplanted when the heart cannot pump effectively.
Benefit: can restore effective circulation and improve quality of life.
Costs and risks: few suitable donors, major surgery, possible rejection and continuing immunosuppressant treatment. Immunosuppression increases susceptibility to infection.
Used occasionally to:
They avoid donor shortage and tissue rejection, but can cause infection or clotting, require power and may wear out.
Choose according to the condition, urgency, likely effectiveness, risks and long-term effects—not by claiming that one category is always best.
For an ‘evaluate’ question, compare benefits and risks in the context given and finish with a justified conclusion. The best treatment may depend on the fault, its severity, donor availability and the patient’s condition.
Develop each point rather than naming it: for example, immunosuppressants reduce rejection but weaken immune responses, increasing the risk of infection.
Do not confuse a replacement heart valve with a whole-heart transplant. A valve replacement treats a faulty valve; a transplant may be used when the heart is failing.
Artificial hearts are not biological transplants, so they are not rejected by the immune system. However, their implantation still requires surgery and can cause infection or blood clots.
It can see this note and what your specification asks for.
Answers are free with an account.
1 free note left this week
Get more free notesYour answer sets when this note comes back for review, or marks it complete.
Was this note helpful?
Log in to tell us whether it helped, or to report a problem.
Last updated
Heart valve
A flap-like structure that opens to let blood move forwards and closes to prevent it flowing backwards.
Faulty heart valve
A heart valve that does not open fully or does not close properly, reducing the efficiency of blood flow through the heart.
Biological valve
A valve made from animal or human tissue that is used to replace a faulty heart valve.
Mechanical valve
An artificial, durable valve used to replace a faulty heart valve.
Heart failure
A condition in which the heart cannot pump blood around the body effectively enough.
Heart transplant
The surgical replacement of a failing heart with a suitable heart from a donor.
Artificial heart
A mechanical device that takes over or supports the heart’s pumping action.
Immunosuppressant
A medicine that reduces the activity of the immune system, helping to prevent rejection of transplanted tissue.
Rejection
An immune response in which the recipient’s body recognises a transplanted organ as foreign and attacks it.
Cardiovascular disease
A disease affecting the heart or blood vessels.
Put your knowledge into practice — try past paper questions for Biology
Heart valve
A flap-like structure that opens to let blood move forwards and closes to prevent it flowing backwards.
Faulty heart valve
A heart valve that does not open fully or does not close properly, reducing the efficiency of blood flow through the heart.
Biological valve
A valve made from animal or human tissue that is used to replace a faulty heart valve.
Mechanical valve
An artificial, durable valve used to replace a faulty heart valve.
Heart failure
A condition in which the heart cannot pump blood around the body effectively enough.
Heart transplant
The surgical replacement of a failing heart with a suitable heart from a donor.
Artificial heart
A mechanical device that takes over or supports the heart’s pumping action.
Immunosuppressant
A medicine that reduces the activity of the immune system, helping to prevent rejection of transplanted tissue.
Rejection
An immune response in which the recipient’s body recognises a transplanted organ as foreign and attacks it.
Cardiovascular disease
A disease affecting the heart or blood vessels.